loading...

by Jennifer Sweeton, PsyD, JD, MS, MA | Nov 11, 2026 | Certificate, Educational
The DBT training cost for mental health professionals ranges from about $60 for a single online CE course to more than $15,000 for a team going through comprehensive DBT training. Most clinicians land somewhere in between. Across the market, a 2-day live workshop usually costs $400 to $900, a 5-day foundational course runs about $1,700 to $1,800 per person, and a formal certification can add several hundred dollars in fees on top of tuition.
Those prices buy very different things. A workshop teaches one skill. A certificate program builds a full foundation you can use with clients right away. Comprehensive training prepares a whole team to run the complete DBT model.
So the smartest budget starts with one question: what do you actually want to do with DBT?
How Much Does DBT Training Cost? A Quick Comparison
Prices in USD, checked November 4, 2026.

Market ranges are based on current listings from established DBT training providers.
| Training option |
Typical market price |
Per clinician or team? |
What you get |
| Individual DBT CE course or workshop |
$60 to $345 for our self-paced DBT courses; $400 to $900 for a 2-day live workshop |
Per clinician |
One focused topic, CE hours, and a certificate of completion |
| Structured DBT skills certificate program |
$650 for our DBT skills certificate program (21.75 CE hours); live skills programs can cost $1,000 or more |
Per clinician |
A full skills curriculum, demonstrations, consultation, and a program certificate |
| Foundational DBT course |
About $1,700 to $1,800 for 5 live days |
Per clinician |
An introduction to the full model, usually for new DBT team members |
| Comprehensive (intensive) DBT training |
$15,000 or more per team of 3 to 8 (roughly $2,000 to $5,500 per person) |
Per team |
Training in the full model, homework, and implementation support |
| Professional DBT certification |
Our certificate program makes you eligible to earn the DBT-PT™ credential at no extra cost (conferred by Mind Works Continuing Education, LLC); board certification for comprehensive DBT, such as DBT-LBC, costs about $870 in fees plus $95 a year |
Per clinician |
A credential reviewed against the issuer’s standards |
★ Recommended Course for This Topic
The EMDR Flash Technique: Processing Trauma Without Flooding
Approved
✓ Board Approved
Credits
1.75 CEUs
Format
Online + Instant Quiz
Price
$53
Get Credits Now →
Instant certificate · 100% online · Accepted by most state licensing boards
What Affects the Price of DBT Training?
The dialectical behavior therapy training cost mostly reflects how much live time, feedback, and team support comes with it. A recorded course can reach thousands of learners at once, while a team intensive needs expert trainers working with one group for days. These factors move the price the most:
- Instructional hours and curriculum depth. A 2-hour course covers one problem. A full program covers all four skill modules and how to apply them.
- Self-paced learning or live workshops. Self-paced courses cost less and fit around a full caseload. Live training adds real-time Q&A, but also a fixed schedule.
- Skills demonstrations, practice, and individualized feedback. Getting feedback on your own cases costs more than watching a demonstration.
- Clinical consultation and implementation support. Comprehensive training often adds months of homework and consultation so a team can launch a program.
- Individual or team-based training. Full DBT is delivered by a team, so intensive training is usually sold to teams, not individuals.
- Training prerequisites. Intensive and foundational courses often require a license or a seat on a DBT team.
- Course access and materials. Some programs lock you out when the cohort ends. Others give lifetime access.
For most DBT training for therapists, the best value comes from training that matches the work you’ll actually do. If you want to use DBT skills with your current clients, you don’t need to pay for a team intensive.
DBT Courses, Certificates, and Certification: What Is the Difference?
They’re three separate outcomes, and each one gives you something different.

Individual DBT Courses and CE Certificates
DBT continuing education courses teach a focused topic and give you CE credit when you finish. CE (continuing education) hours are what licensing boards count toward license renewal. You’ll get a certificate of completion for your records, which is great for renewal but isn’t a credential.
DBT Skills Certificate Programs
A DBT certificate program links several courses into one structured path, and you earn a program certificate at the end. It’s a strong fit for DBT-informed therapy, where clinicians bring mindfulness, distress tolerance, emotion regulation, and interpersonal effectiveness skills into their regular sessions. These skills overlap with other mindfulness-based approaches, so if you’re choosing a training path, it helps to compare ACT therapy vs DBT first.
That’s different from running full DBT. As Marsha Linehan designed it, comprehensive DBT combines individual therapy, weekly skills training groups, phone coaching, and a DBT consultation team.
The full model has a strong research base. In a 2006 randomized trial of 101 women with recent suicidal behavior, those in DBT were half as likely to attempt suicide as those treated by community experts. Still, many clinicians don’t work in a full DBT program, and DBT skills training gives them practical tools they can use with clients right away.
Professional DBT Certification
Certification is a review against an organization’s standards, and professional credentials from different issuers aren’t interchangeable.

Board certification for comprehensive DBT has strict certification requirements, including a year on a DBT consultation team, an exam, and recorded sessions. DBT-LBC accepts its 40 required didactic training hours from any training organization, including online CE courses, so DBT coursework like ours can go toward that requirement. That route makes sense if you already work on a full DBT team.
If you want a credential that reflects applied DBT skills training, our program offers a more direct path. Clinicians in practice who complete our full certificate curriculum become eligible for the DBT-PT™ credential and digital badge, conferred by Mind Works Continuing Education, LLC, our independent certification body. It comes at no extra cost and has no recertification fees: it renews free every 4 years by simple attestation.
What Additional DBT Training Expenses Should You Budget For?
Tuition fees rarely cover everything, especially for live or credential-focused training. Plan for:
- Travel, lodging, and meals if any part of the training is in person.
- Books and materials, such as a DBT skills training manual.
- Extra consultation and feedback beyond what the course includes.
- Application fees and exam costs. The DBT certification cost for formal board certification usually runs several hundred dollars across separate application, exam, and review fees.
- Renewal fees, sometimes charged every year, plus extra CE hours to stay certified.
- Time away from paid clinical work, which for a 5-day live course can cost more than the tuition.
Self-paced online training cuts most of these costs. There’s no travel, no missed sessions with clients, and with our DBT-PT™ credential, no renewal fees.
Online CE Credits Has DBT Training Options That Fit Your Goals and Budget
| Your goal |
Your best fit |
| Explore DBT or study one skill |
A single online course with CE credit |
| Build a broader foundation in DBT-informed work |
Our DBT skills certificate program |
| Earn a DBT credential without board-level fees |
The certificate program, plus eligibility for the DBT-PT™ credential at no extra cost |
| Prepare to implement comprehensive DBT |
Team training in the full model |
| Earn CE while developing existing skills |
Topic-focused courses at the right instructional level |
For clinicians who want affordable DBT training they can use right away, our online DBT continuing education courses are a practical start. They’re NBCC and ASWB approved, and most are priced at $30 per CE hour. A course on reactive, treatment-resistant clients costs $75 for 2.5 CE hours, and our 11.5-hour DBT symposium costs $345.
The DBT skills certificate program (the Certificate in DBT Skills and Clinical Applications) goes further for $650, about what many 2-day live workshops cost. It bundles four courses (21.75 CE hours) covering the core skills, DBT for PTSD, resistant clients, and suicide risk assessment with the L-RAMP.
You learn from instructors including Stanford-trained psychologist Emily Wharton, PsyD; Ashley Garrison, LCSW, who delivers an adherent DBT program and takes part in a weekly consultation team; and Kimberly Duris, EdD, LCPC, who teaches the resistant clients course. You also get free admission to up to four 1-hour consultation groups for your toughest cases, lifetime access, a program certificate, and the DBT-PT™ credential pathway at no extra cost.
FAQs
How much does online DBT training cost?
Live online DBT workshops often run $400 to $900 for two days. Self-paced courses cost much less: ours range from $60 to $345, and our 21.75-CE certificate program costs $650.
Is DBT certification included in the training price?
Usually not. Formal certifications are typically billed separately, with application, exam, and renewal fees. Our certificate program is different. If you complete the full curriculum, you’re eligible to earn the DBT-PT™ credential at no extra cost (conferred by Mind Works Continuing Education, LLC), and it has no recertification fees.
Is a DBT certificate the same as DBT certification?
No. A certificate shows you completed a curriculum. Certification means a named organization reviewed you against its standards, often including an exam, supervised practice, or recorded sessions.
Can I pay for DBT training in installments?
Sometimes, though payment plans vary by provider. Our certificate program offers 4 monthly payments of $162.50, which totals $650, the same as paying upfront, and you get access to the full program after your first payment.
Do DBT training courses count toward continuing education requirements?
They can, if the course is approved for your profession and your licensing board accepts it. Our courses carry NBCC and ASWB approval, but you should still check your CE requirements by state and profession before you buy.

by Tim Cassidy, MBA, MA, LPC | Mar 10, 2025 | Educational
For mental health professionals, understanding the brain can unlock powerful insights into client care. In The Neuroscience Handbook for Clinicians by Dr. Jennifer Sweeton, the thalamus emerges as a critical, often overlooked brain region in trauma therapy. As a “relay station” for sensory information, the thalamus plays a pivotal role in how clients experience PTSD symptoms like re-experiencing and dissociation. Let’s explore its functions, impact on trauma, and how you can apply this knowledge in your practice, and how our CE courses at Online CE Credits can help.
What Is the Thalamus and Why It Matters
The thalamus, a small egg-shaped structure above the brain stem, acts as the brain’s sensory gatekeeper, relaying sensory inputs (except smell) to regions like the amygdala (threat detection) and cortex (executive functioning).
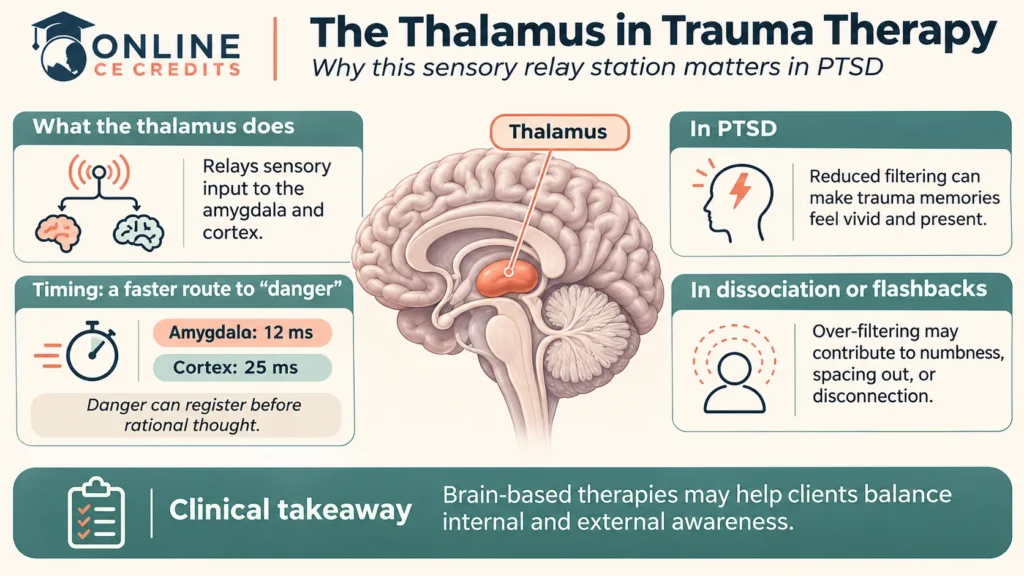
That sensory information reaches the amygdala in just 12 milliseconds, which is half the time it takes to reach the cortex (25 milliseconds). This means clients often process danger before rational thought kicks in, a key factor in trauma responses.
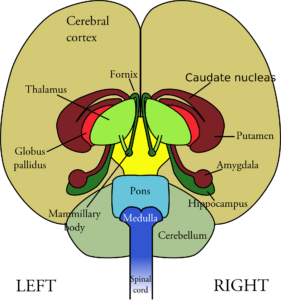
The Thalamus in Trauma: Symptoms and Challenges
Research (e.g., Etkin & Wager, 2007; Kim et al., 2007) shows that individuals with PTSD often exhibit thalamic hypoactivation at rest and during re-experiencing symptoms, such as traumatic sensory re-enactments. This reduced activation disrupts sensory filtering, making trauma memories feel vivid and present, as if the event is happening now. And, there is weaker connectivity between the thalamus and amygdala in severe PTSD, exacerbating these symptoms (Zhu et al., 2017). Conversely, during dissociation or flashbacks, the thalamus becomes hyperactive, over-filtering sensory input, leading to numbness or disconnection. When this happens, clients may appear “spacey” or detached, per Lanius et al. (2001).
Applying Neuroscience to Trauma Therapy
Understanding the thalamus’s role can transform your approach. Research has shown that Eye Movement Desensitization and Reprocessing (EMDR) activates the thalamus through bilateral eye movements, helping clients better filter sensory information and integrate traumatic experiences (Bergmann, 2008).

This reduces the intensity of re-experiencing symptoms by balancing internal and external awareness. Cognitive Behavioral Therapy (CBT) also shows promise, increasing thalamus activation and reducing PTSD symptoms, per Peres et al. (2007). These brain-based strategies can guide your treatment planning, ensuring client-centered care grounded in neuroscience.
Earn CE Credits with Online CE Credits
At Online CE Credits, we offer NBCC- and ASEB-approved courses to deepen your neuroscience-based practice. With over 250 on-demand courses, you can learn 24/7, earning credits at your pace. Explore our trauma-focused CE programs and start transforming your practice today!
Conclusion
The thalamus’s role in sensory processing makes it a key player in trauma therapy. By understanding its impact on PTSD symptoms and leveraging therapies like EMDR and CBT, you can help clients heal more effectively. Explore these insights further with Online CE Credits and take your practice to the next level.

by Tim Cassidy, MBA, MA, LPC | Feb 11, 2026 | Educational
A client can look fine in session, then go home and shut down for hours. They know what happened. They can explain the pattern. But inside, it still feels like two forces are pulling at once.
That push and pull is the exact problem IFS is trying to solve. Instead of debating the “right” feeling, it maps what is happening in the client’s inner world in real time.
Below, we explain what IFS therapy is, what parts actually mean in clinical work, and when it fits best.
What IFS Therapy Actually Is (Plain-English Explanation)

IFS therapy is a structured therapy model that treats the mind like an internal system made of “parts.” Each part has a job, even when its behavior causes problems.
In session, the therapist helps the client meet these parts with less fear and more self-compassion, so the person can respond with choice instead of panic.
This approach is called Internal Family Systems (IFS therapy), created by Richard Schwartz.
The Core Components of IFS (Parts + Self)
IFS is not saying someone has “multiple personalities.” It is saying most people have different inner reactions that can feel like different voices. The IFS model uses clear categories:
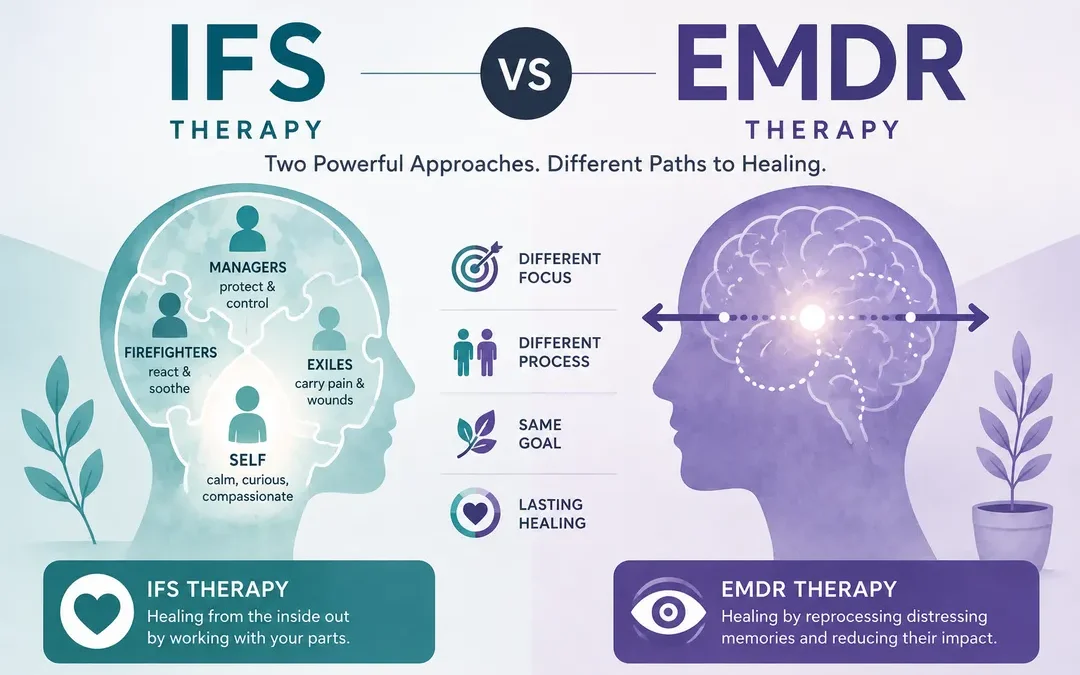
- Exiles: parts that carry emotional pain, fear, shame, and grief. They often hold multiple childhood trauma memories or unmet needs.
- Managers: parts that try to prevent pain. They may push perfectionism, control, overthinking, or people pleasing.
- Firefighters: parts that act fast when pain breaks through. They may numb, distract, shut down, binge, or rage.
- The Self: the core self, a steady state marked by calm, curiosity, clarity, and care. In IFS, the goal is self-leadership, not “getting rid” of parts.
What IFS Therapy Is Used For (And When It Fits Best)
IFS focuses on inner conflict patterns, not just symptom labels. It can be a strong fit when clients have insight, yet still feel stuck. It is often used in trauma and attachment work, and in family therapy settings, since parts often formed in relationships.
It is often a “best fit” approach for:
- Developmental and complex trauma
- Chronic anxiety and inner conflict
- Shame cycles and harsh self-criticism
- Attachment wounds affecting personal and intimate relationships
- Clients with difficult emotions that flip fast, or feel “too much”
- Clients who keep understanding the story, but still feel unsafe inside
IFS vs Traditional Talk Therapy (Why It Feels Different)

Traditional talk therapy can help a client explain what happened and name triggers. IFS often shifts the focus from “Why am I like this?” to “Which part is doing this, and what is it protecting?”
In many humanistic and psychodynamic therapy styles, the relationship and meaning are central, and insight is a big lever.
IFS still values the relationship, but it adds a step-by-step IFS process for working with inner protectors.
The therapist does not debate the part. The therapist gets curious about their role. Over time, clients often report more inner harmony because parts stop fighting for control.
Is IFS Therapy Evidence-Based and Trauma-Informed?

IFS has a growing research base, but it is not as large as CBT. The fairest way to say it is that the evidence is promising and still developing.
A review from the Australian Psychological Society describes IFS as a trauma-informed model that has been used across clinical settings, with early studies that suggest benefit for trauma-related symptoms.
There is also newer research looking at IFS concepts in relation to posttraumatic stress disorder and complex trauma symptoms in adults. One 2025 paper (survey design) examined IFS-informed concepts like parts and self-leadership in a large adult sample, linking these constructs to trauma symptom patterns.
What Therapists Should Know Before Using IFS
IFS is a full clinical model with fair pricing, not a casual parts exercise. A therapist needs more than a script. They need solid pacing, consent, and a plan for what happens when emotions spike.
Ethically, IFS use includes training and consultation, like other trauma approaches. This matters more with dissociation risk and complex trauma, where “going inside” too fast can flood an exile and trigger firefighter reactions.
That is also why many clinicians pursue IFS training through CE courses. It gives a clear pathway, with skills practice, feedback, and a place to ask hard case questions.
If you’re a clinician who wants a structured way to build confidence, our IFS courses on OnlineCECredits can support that growth.
FAQ
What is IFS therapy in simple terms?
Internal Family Systems therapy helps clients meet inner “parts” with curiosity, then lead with the calm Self. Symptoms often soften when protectors feel heard, not fought.
Is IFS only for trauma?
No. It is often used for trauma, but it also fits anxiety, shame, and inner conflict. It can help clients who feel stuck, even with good insight.
Can IFS be done online?
Yes, when privacy and safety are strong. Online sessions can work well for parts work, as long as the IFS therapist has a clear plan for grounding, pacing, and crisis steps.
How is IFS different from EMDR or CBT?
CBT targets thoughts and behavior patterns. EMDR targets distressing memories with a structured reprocessing method. IFS targets the inner system of parts and self-leadership. Read more: CBT vs. EMDR therapy
Do therapists need training to use IFS?
They should. IFS is structured, and trauma cases can get intense. Training and consultation help therapists pace safely, work with protectors, and handle dissociation risk.
What is IFS therapy used to treat?
It is used for mental health concerns like anxiety, shame, trauma symptoms, relationship patterns, and sometimes depressive symptoms, especially when inner conflict drives the cycle.
What is the IFS therapy controversy?
Some clinicians feel “parts language” can be misunderstood or used too loosely. Others debate the size of the research base. The safest stance is careful training and a clear scope.
What are the 6 steps of IFS therapy?
Many clinicians describe a flow like: notice a part, separate from it (unblend), get curious, learn its role, witness its burden, then support new choices. But the terms vary by training.
by Tim Cassidy, MBA, MA, LPC | Aug 5, 2026 | Educational
Two clients can carry trauma very differently. One keeps reliving a specific memory, while another feels divided between fear, shame, control, and avoidance.
That difference matters when comparing IFS vs EMDR therapy. Both approaches may support healing trauma, but they enter the work through different clinical doors.
IFS vs EMDR Therapy
IFS therapy works with the client’s internal system of protective and wounded parts. While EMDR therapy uses a structured process to help clients reprocess traumatic memories and reduce their emotional charge.
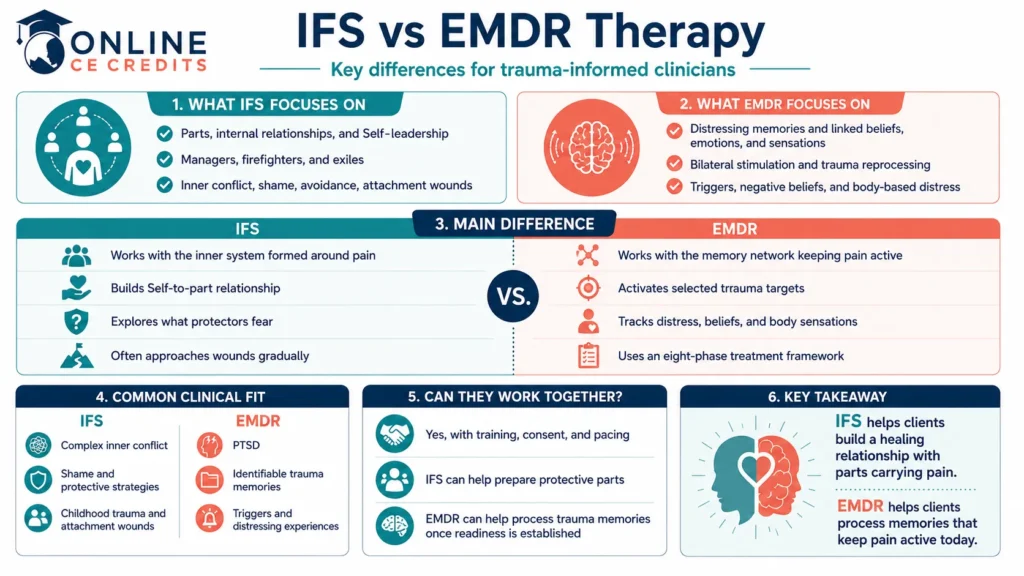
Internal Family Systems vs EMDR is therefore less about choosing a winner and more about identifying the treatment target.
| Category |
IFS Therapy |
EMDR Therapy |
| Full name |
Internal Family Systems therapy |
Eye Movement Desensitization and Reprocessing |
| Main focus |
Parts, internal relationships, and Self-leadership |
Distressing memories and linked beliefs, emotions, and sensations |
| Core idea |
Parts carry protective roles, wounds, fears, and learned strategies |
Traumatic memories may remain easily activated and poorly integrated |
| Main clinical target |
Internal conflict, shame, avoidance, attachment wounds, and protective patterns |
Trauma memories, triggers, negative beliefs, and body-based distress |
| Common language |
Parts, Self, exiles, managers, firefighters, blending, and unburdening |
Targets, bilateral stimulation, desensitization, cognitions, and body scan |
| Session style |
Relational, exploratory, and experiential |
Structured, phase-based, and focused on memory processing |
| Trauma discussion |
Vulnerable material may be approached gradually through protectors |
Clients focus on targets, although detailed verbal retelling is usually unnecessary |
| Evidence base |
Growing, with newer trials and major research gaps remaining |
Well-established and guideline-supported for PTSD |
| Common clinical fit |
Complex inner conflict, shame, childhood trauma, and protective strategies |
PTSD, identifiable trauma memories, triggers, and distressing experiences |
| Integration |
May prepare protective parts for deeper trauma work |
May process memories once readiness and stability are established |
Clinicians who want to explore either model further can browse our IFS courses and EMDR courses for practical, trauma-informed training.
What Is IFS Therapy?
Internal Family Systems is a therapy approach developed by Richard Schwartz that views the mind as naturally containing different parts. These parts are not treated as broken personalities. Each part developed feelings, beliefs, or behaviors that once served a purpose.
For example:
- Managers try to prevent pain through control, perfectionism, planning, or emotional distance…
- Firefighters react quickly when pain breaks through, sometimes using anger, numbing, avoidance, or impulsive behavior…
- Exiles carry older fear, shame, grief, and trauma wounds.
The IFS model helps clients approach these parts with curiosity and compassion. The wider goal is Self-leadership, where calm, clarity, connection, and choice guide the internal system.
Read more: IFS training cost
What Is EMDR Therapy?
EMDR stands for Eye Movement Desensitization and Reprocessing. It is a structured trauma therapy designed to process traumatic memories and their connected beliefs, emotions, images, and physical sensations.

During EMDR sessions, a client recalls part of a distressing experience while attending to alternating bilateral stimulation. This may involve guided eye movements, taps, or tones.
EMDR follows eight phases covering history, preparation, assessment, desensitization, installation, body scan, closure, and reevaluation.
The Main Difference Between IFS and EMDR
The clearest difference is what each approach organizes the session around. IFS focuses on the inner system that formed around pain. EMDR focuses on the memory network keeping that pain active.
IFS asks, “Which part carries this fear, shame, anger, or need for protection?” EMDR asks, “Which memory, belief, emotion, and body sensation need reprocessing?”
| IFS |
EMDR |
| Builds a Self-to-part relationship |
Activates a selected trauma target |
| Explores what protectors fear might happen |
Tracks distress, beliefs, and physical sensations |
| May map managers, firefighters, exiles, and polarized parts |
Sequences past memories, current triggers, and future situations |
| Often earns protector trust before approaching wounds |
Begins trauma reprocessing after preparation and readiness |
| Uses compassion, unblending, witnessing, and unburdening |
Uses dual attention and bilateral stimulation |
| Follows the client’s internal system |
Follows an eight-phase treatment framework |
IFS helps clients build a healing relationship with parts carrying pain. EMDR helps clients process memories that keep pain active today.
IFS vs EMDR for PTSD
EMDR has the stronger established evidence base for PTSD. VA/DoD places EMDR alongside Prolonged Exposure and Cognitive Processing Therapy among the most effective trauma-focused treatments.
IFS research is newer, although it has moved beyond case reports. A 2025 scoping review mapped 27 peer-reviewed studies and described IFS as promising for PTSD, depression, chronic pain, and self-compassion. However, only two included studies were randomized trials, leaving important evidence gaps.
Also, a 2026 randomized trial found greater PTSD symptom improvement from an online, group-based IFS program than its comparison condition. This adds meaningful evidence, but does not yet place IFS beside guideline-supported PTSD treatments.
Clinically, EMDR may fit identifiable trauma targets. IFS may help when protective parts, shame, avoidance, or internal conflict interfere with direct trauma work.
IFS vs EMDR for Complex Trauma
Both approaches may support complex trauma treatment, but readiness often matters more than modality preference.
Complex trauma may involve childhood trauma, attachment wounds, dissociation, emotional dysregulation, shame, conflicting trauma responses, and strong protector strategies.
- IFS can help the therapist understand which parts fear deeper trauma processing and what they need before proceeding.
- EMDR can reprocess traumatic memories within a wider treatment plan, but preparation, resourcing, and careful target selection remain essential.
A 2025 clinical perspective proposed combining IFS-informed preparation with EMDR for severe dissociation. However, the paper presented a theoretical framework rather than a clinical trial.
For complex trauma, the central question is often what the client’s nervous system and inner system need before deeper processing begins.
IFS vs EMDR for Anxiety and Depression
IFS therapy vs EMDR therapy depends on what appears to drive the anxiety or depression.
IFS may help when anxiety involves controlling managers, alarmed protectors, avoidant parts, or firefighters trying to stop emotional overwhelm. With depression, IFS may explore hopeless parts, harsh inner critics, shame-carrying exiles, or protectors that withdraw from relationships.
EMDR may fit when symptoms connect clearly to distressing memories, grief, humiliation, attachment injuries, or negative beliefs. An EMDR therapist might target the experience linked to “I am unsafe” or “I am worthless,” then track how its emotional charge changes.
IFS vs EMDR Techniques
IFS mainly works through internal relationships, while EMDR organizes trauma work around memory networks.
| Clinical Focus |
IFS Technique or Concept |
EMDR Technique or Concept |
| Trauma memory |
Witnessing exile experiences and unburdening |
Processing a selected target memory |
| Emotional overwhelm |
Unblending and building Self-energy |
Preparation, resourcing, pacing, and closure |
| Self-criticism |
Understanding the critic’s protective role |
Reprocessing memories linked to negative cognition |
| Avoidance |
Exploring what protectors fear |
Targeting memories and triggers tied to avoidance |
| Shame |
Compassionate Self-to-part relationship |
Reprocessing shame-linked memories and beliefs |
| Dissociation |
Protector permission and internal cooperation |
Stabilization and readiness before processing |
| Triggers |
Mapping which parts become activated |
Processing earlier events linked to current triggers |
| Body sensations |
Exploring sensations carried by parts |
Tracking sensations and completing the body scan |
| Internal conflict |
Working with polarized parts |
Sequencing multiple linked targets |
What Happens in an IFS Session?
An IFS session usually starts with the strongest inner reaction showing up in the moment. The therapist helps the client slow it down, identify which part is active, and understand what that part fears or protects.
- The client notices an active part. This might appear as tension, criticism, fear, numbness, anger, or an urge to leave.
- The therapist invites curiosity. The client observes where the part appears and how they currently feel toward it.
- Other reactions are separated. If one part hates or fears another, the therapist may help it step back temporarily.
- The part explains its role. The client explores what it does, what it fears, and whom it believes it protects.
- Protectors build trust. Managers or firefighters may need reassurance before allowing contact with vulnerable material.
- Wounded parts may become accessible. Exiles can share emotions, memories, beliefs, and unmet needs without being rushed.
- The work moves toward unburdening. Using IFS, clients may release old shame, fear, or beliefs carried by wounded parts.
Is IFS or EMDR Better Overall?
Neither approach is automatically better overall. The stronger fit depends on symptoms, readiness, goals, stability, and case conceptualization.
| Clinical Situation |
Possible Fit |
| Clear and distressing trauma memories |
EMDR may offer a more direct trauma reprocessing path |
| Strong inner conflict or protective behavior |
IFS may provide a useful map for parts work |
| Complex trauma and attachment wounds |
Both may serve different stages of treatment |
| High dissociation or instability |
Stabilization should come before modality preference |
| Multiple connected trauma targets |
EMDR target sequencing may help organize treatment |
| Parts resisting trauma processing |
IFS may clarify fear and build internal permission |
Can IFS and EMDR Be Used Together?
Yes, clinicians can integrate IFS and EMDR, but the combination needs clear reasoning, training, consent, and pacing.
IFS can identify protectors that fear trauma treatment or expect the client to become overwhelmed. The therapist may work with those parts before beginning EMDR desensitization. EMDR can later help reprocess traumatic memories carried by vulnerable parts.
This integration should never become a loose collection of techniques. Clinicians need competence in both models and should explain why each intervention belongs in the treatment plan.
What Therapists Should Know About IFS vs EMDR
IFS should not be reduced to simply “talking to parts,” and EMDR involves far more than following eye movements.
EMDR focuses on structured assessment, preparation, target selection, processing, closure, and reevaluation. IFS focuses on internal relationships, protection, unblending, Self-leadership, and the healing process between Self and parts.
The evidence also differs.
EMDR has broad guideline support for PTSD, while IFS research remains smaller despite encouraging recent trials. A 2025 study of 697 adults examined links between childhood trauma, IFS concepts, PTSD symptoms, and disturbances in self-organization. Such findings support continued research, but they do not establish treatment effectiveness.
Good trauma-informed care still depends on ethics, consultation, case conceptualization, and client-centered pacing.
Learn Trauma Therapy Skills With Online CE Credits
Trauma clients rarely arrive with one clean symptom or one simple memory. Clinicians, therefore, need education that supports the difficult decisions between preparation, parts work, stabilization, and trauma reprocessing.
At Online CE Credits, we offer flexible IFS courses covering protectors, exiles, polarized parts, shame, anxiety, attachment, and trauma-informed therapy. We also have EMDR courses with training on all eight phases, complex trauma, dissociation, anxiety, depression, telehealth, children, and protocol modifications.
Clinicians seeking a structured path can explore our 23-CE foundational EMDR certificate or 32-CE advanced program. Both support flexible online learning, practical skills, and consultation opportunities for counselors, social workers, therapists, psychologists, and MFTs.
FAQ
Is IFS the same as EMDR?
No. IFS works with parts, Self-leadership, and internal relationships. EMDR uses bilateral stimulation within a structured process for distressing memories.
Is IFS or EMDR better for trauma?
It depends on the treatment target. EMDR has stronger PTSD evidence, while IFS may help with protectors, shame, avoidance, and inner conflict.
Can IFS and EMDR be combined?
Yes. IFS may prepare protective parts for trauma work, while EMDR may process memories carried by vulnerable parts. Integration requires training and consent.
Is EMDR more evidence-based than IFS?
For PTSD, yes. EMDR has stronger research and clinical guideline support. IFS evidence is growing, but the research base remains less mature.
Is IFS good for complex trauma?
IFS is often applied to complex trauma involving shame, attachment wounds, protectors, and internal conflict. Current studies are promising, although more rigorous research remains necessary.
Does EMDR require talking about trauma in detail?
Usually not. Clients focus on the trauma memory, but detailed verbal retelling is generally unnecessary during EMDR.

by Tim Cassidy, MBA, MA, LPC | Nov 4, 2026 | Certificate, Educational
The Internal Family Systems training cost for mental health professionals runs from about $60 to more than $7,000, depending on what they’re actually buying. A single online CE course on parts work usually costs under $200. A structured independent certificate program can run several hundred dollars. Official IFS Institute Level 1 training currently starts around $4,200 for U.S. online cohorts.
Those options lead to different places. Finishing a CE course, completing Institute training, and earning IFS certification are three separate outcomes, so the cheapest path only makes sense if it gets someone where they want to go.
How Much Does IFS Training Cost? A Quick Comparison
Institute tuition is set per cohort, so the figures below are representative examples, not one fixed price.
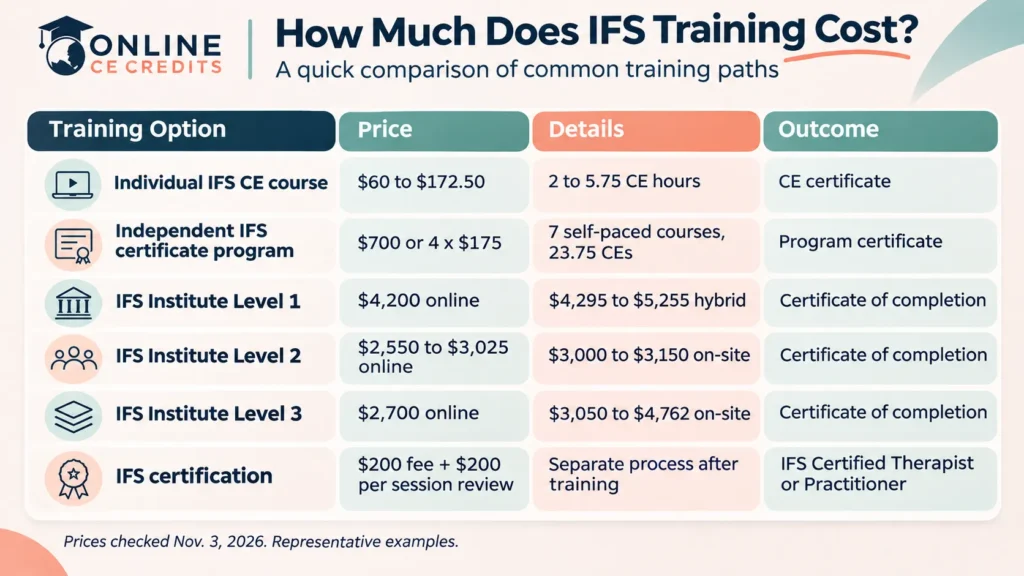
Prices checked November 3, 2026.
| Training option |
Current price |
What it includes |
Credential or outcome |
| Individual IFS CE course |
$60 to $172.50 for 2 to 5.75 CE hours (our IFS courses) |
Recorded training on one topic, such as shame, couples, or complex trauma |
CE certificate after the quiz and evaluation; lifetime access when bought outright |
| Independent IFS certificate program |
$700, or 4 payments of $175 (our IFS certificate program) |
7 self-paced courses, 23.75 CE hours, up to four 1-hour consultation groups |
Program-level certificate; eligible to earn the IFS-PT™ credential at no extra cost (conferred by Mind Works Continuing Education, LLC). Not IFS Institute training |
| IFS Institute Level 1 |
$4,200 for most U.S. online cohorts; $4,295 to $5,255 for hybrid cohorts (Level 1 listings) |
About 90 hours of live foundational training with small practice groups |
Institute certificate of completion; CE hours offered for most cohorts |
| IFS Institute Level 2 |
$2,550 to $3,025 online; $3,000 to $3,150 on-site (Level 2 listings) |
Topic-based advanced training, such as trauma, addictions, or shame |
Certificate of completion; one of the routes toward certification |
| IFS Institute Level 3 |
$2,700 online; $3,050 to $4,762 on-site (Level 3 listings) |
Intensive work with other advanced practitioners |
Certificate of completion |
| IFS certification |
$200 certification fee, plus $200 per session review (Institute fees) |
A separate credentialing process after training |
IFS Certified Therapist or Practitioner; $150 to recertify every 2 years |
What Are You Paying for in an IFS Training Program?
Two programs can share the word “IFS” and still give clinicians very different things. These details move the price:
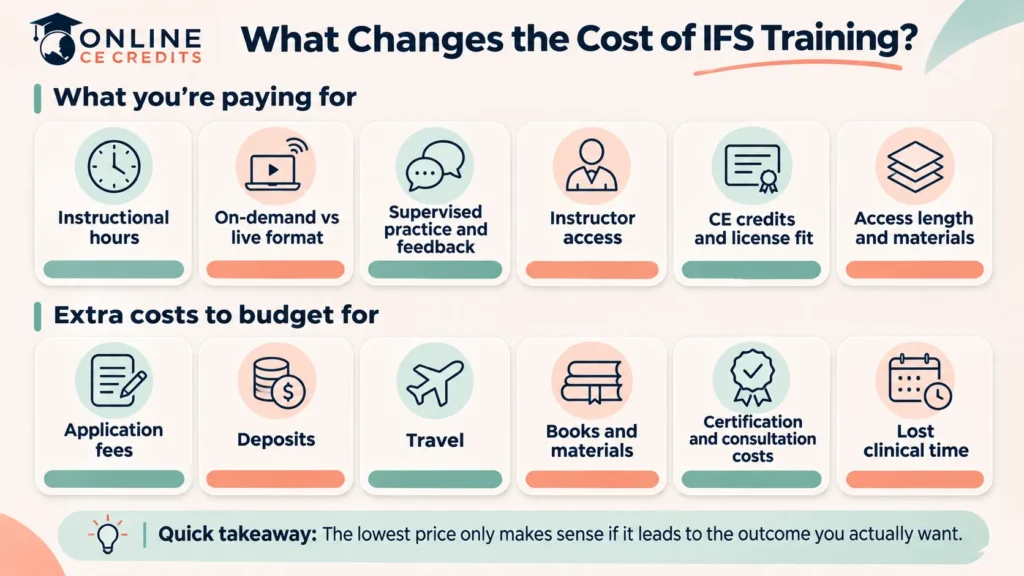
- Total instructional hours and whether the content is introductory or advanced.
- On-demand courses versus scheduled live workshops.
- Supervised practice, feedback, and experiential learning, meaning learning through exercises and personal experience.
- Instructor contact and practice-group size.
- CE credits and acceptance for their license.
- Access duration, handouts, and other supporting materials.
What Is the Difference Between IFS CE Courses and Official Institute Training?

They lead to different outcomes, and the IFS Institute treats them separately. Each one answers a different need:
- Independent CE courses teach IFS concepts or applications and give CE credit where approved. They’re education, not a credential.
- Provider-issued certificate programs show that someone finished that provider’s curriculum. The certificate belongs to the provider, not to the Institute.
- Official IFS Institute training is the Institute’s own Level 1, 2, and 3 pathway, created around the model developed by Richard Schwartz, PhD.
- IFS certification is its own process. The Institute states clearly that earning a Level 1 certificate of completion is not the same as being IFS Certified.
At Online CE Credits, we offer the first two. Our IFS courses cover topics like shame, couples, men’s work, and dissociation, with instructors including psychiatrist Frank Anderson, MD. They’re NBCC and ASWB approved and priced at $30 per CE hour. Our Certificate in IFS Skills for Trauma & Advanced Integrations brings seven of those courses into one structured path and includes free admission to up to four 1-hour consultation groups. Clinicians who complete it are eligible to earn the IFS-PT™ credential at no extra cost, conferred by Mind Works Continuing Education, LLC. Unlike Institute certification, which costs $150 to renew every 2 years, IFS-PT™ has no recertification fees: it renews free every 4 years by attestation. The program is independent of the IFS Institute and doesn’t count toward Institute training or certification.
The research is still developing, too. A 2026 randomized trial of an online group IFS program for PTSD found it was feasible and well accepted, with patients attending more sessions than the comparison group. Both groups improved, with no significant difference between them.
What Additional Costs Should You Budget For?

Tuition fees are only part of the bill for official training. Plan for these training expenses as well:
- Application fees. The Institute charges a $75 non-refundable General Application fee for each training level.
- Deposits. A $500 non-refundable deposit is due at registration and counts toward tuition.
- Travel. Hybrid and on-site cohorts don’t include travel, lodging, or meals.
- Books and materials. Level 1 brochures list required reading, and trainers may ask for up to $30 in extra materials.
- Credential costs. The IFS certification cost goes beyond the $200 fee. It adds consultation hours with an Approved Clinical Consultant, billed at that consultant’s own rate, plus session review fees.
- Lost clinical time. Live sessions often run on weekdays, which can mean fewer paid client hours.
- CE fees. Institute CE is offered at no extra fee for most Level 1, 2, and 3 trainings, but other providers may charge separately.
Which IFS Training Option Fits Your Goals and Budget?

Start with the outcome you want, then compare the options that actually lead there.
| Your goal |
What to compare |
| Explore IFS with affordable IFS training before committing thousands |
Short introductory courses, learning objectives, instructor background, and price per CE hour |
| Earn CE while studying a specific clinical topic |
Course topic, CE hours, and whether the approval fits your license and state |
| Follow a structured independent program |
Number of courses, consultation included, access length, and exactly what the certificate wording claims |
| Become eligible for official IFS certification |
Institute training prerequisites, Level 1 and Level 2 tuition, 2 years and 200 hours of IFS practice, and consultation costs |
Whichever route someone chooses, finishing a course or program doesn’t prove competence with every client. It also doesn’t expand a clinician’s scope of practice, which still comes from their license.
Clinicians interested in independent continuing education can browse our IFS course collection to compare topics, CE hours, formats, and current prices.
FAQs
How much does IFS Level 1 training cost?
Most current U.S. online Level 1 cohorts list tuition of $4,200, such as the Mountain Time cohort starting February 2027. Hybrid cohorts run $4,295 to $5,255 because they add on-site sessions, and some Canadian online cohorts list $3,200 to $3,350 USD. The $75 application fee comes on top.
Is IFS certification included in the cost of training?
No. Certification is a separate step, and the current certification requirements include Level 1 plus Level 2 (or assisting a Level 1), at least 2 years and 200 hours of IFS practice, 15 IFS CE hours, 15 consultation hours, and a reviewed session. Fees include $200 for certification and $200 per session review.
Are online IFS courses cheaper than in-person training?
Usually, yes. Online IFS training through the Institute skips travel and lodging, and on-demand courses cost far less again. In-person and hybrid cohorts add face-to-face practice and feedback, which some clinicians value enough to pay for.
Do IFS continuing education courses count toward Institute certification?
Not automatically. The Institute only accepts certain advanced IFS programs as IFS continuing education. Our courses and certificate program are independent and don’t qualify for IFS Institute credits or certification, so check the official requirements before planning around any course.
Are scholarships or payment plans available for IFS training?
It depends on the provider. The IFS Institute offers limited partial scholarships based on diversity and economic need (household income at or below $90,000), and it doesn’t offer payment plans, though early partial payments are allowed. Our certificate program offers 4 monthly payments of $175.

by Jennifer Sweeton, PsyD, JD, MS, MA | Mar 10, 2025 | Educational
Trauma therapy can produce meaningful change, but no single treatment approach works equally well for every client.
Evidence-based approaches such as cognitive behavioral therapy (CBT), exposure therapy, EMDR, and other trauma-focused treatments can be highly effective. Yet clinicians working with PTSD and complex trauma will inevitably encounter clients who become overwhelmed during processing, dissociate, struggle to connect cognitive insights with physical reactions, or simply stop progressing.
That does not necessarily mean trauma therapy has failed. It may mean the client needs a different pace, additional stabilization, or a more flexible combination of therapeutic tools.
This is one of the clinical gaps Neural Desensitization and Integration Training (NDIT) was designed to address.
Why Can Traditional Trauma Therapy Stall?
Trauma affects more than what a client thinks about a distressing experience. It can influence emotional regulation, threat responses, memory, attention, relationships, and physical reactions to perceived danger.

This helps explain why a client can understand their trauma intellectually while continuing to react as though the threat is still present.
Clinicians interested in this distinction can see how the approaches differ in our comparison of EMDR vs traditional talk therapy.
Several challenges commonly emerge during trauma treatment.
1. Trauma Processing Can Become Overwhelming
Exposure-based interventions require clients to engage with distressing memories or reminders. For some clients, however, processing traumatic material too intensely can produce emotional flooding rather than productive therapeutic engagement.
Clinicians may need to adjust the speed, intensity, or structure of trauma processing according to the client’s response.
This is particularly important when working with complicated presentations. Our Advanced EMDR Skills for Complex Trauma course explores modifications clinicians can use when dissociation, attachment trauma, overwhelm, or stuck processing complicate standard EMDR work.
2. Clients May Dissociate or Shut Down
Not every trauma response presents as visible anxiety or panic.
Some clients disconnect from emotions, bodily sensations, memories, or their surroundings. Others may appear calm while having difficulty remaining emotionally engaged with traumatic material.
In these cases, moving directly into intensive trauma processing may not be appropriate. Treatment may first require grounding, stabilization, body awareness, and improved nervous system regulation.
Understanding how trauma affects sensory processing can also give clinicians additional context. For example, the role of the thalamus in PTSD helps illustrate why sensory information, threat responses, and trauma symptoms can remain closely connected.
3. Cognitive Insight Does Not Always Change the Trauma Response
A client may know that an event happened years ago. They may understand their triggers and recognize that they are currently safe.
Yet their nervous system may still react automatically.
A smell, sound, facial expression, location, or physical sensation can activate an intense response before the client has time to consciously interpret what is happening.
Cognitive approaches remain valuable, but some trauma presentations require clinicians to work with emotional, physiological, sensory, and memory-based processes as well.
4. One Protocol May Not Fit Every Client
Structured trauma treatments provide clinicians with important evidence-based frameworks. The challenge comes when a protocol is applied too rigidly to clients whose symptoms or circumstances require greater flexibility.
Complex trauma, chronic dissociation, attachment difficulties, multiple traumatic experiences, and co-occurring disorders can all complicate treatment.
Even clinicians deciding whether a highly structured modality fits their practice may benefit from considering the advantages and limitations discussed in Is EMDR Training Worth It?.
The issue is not that structured therapies are ineffective. It is that clinicians may need more than one set of tools.
How Can NDIT Fill Some of These Gaps?
Neural Desensitization and Integration Training (NDIT) is an evidence-informed, trauma-focused framework developed by clinical psychologist and neuroscientist Dr. Jennifer Sweeton.

Rather than functioning as one rigid protocol, NDIT uses a module-based approach that integrates concepts and techniques from established trauma therapies, including EMDR, exposure-based approaches, IFS, cognitive interventions, and other trauma-focused methods.
The goal is not to replace the approaches clinicians already use.
Instead, NDIT gives therapists another framework for deciding what a particular client may need, when they may need it, and how intensely trauma material should be processed.
1. Regulation Before Intensive Processing
For clients who quickly become emotionally flooded, beginning with intensive trauma processing may create unnecessary difficulty.
NDIT emphasizes skills that can help clinicians prepare clients for deeper trauma work and regulate activation during the process.
The underlying principle is straightforward: trauma processing should be challenging enough to engage the memory without becoming so intense that the client can no longer participate effectively.
2. Titrating Exposure to Traumatic Material
Exposure remains an important component of many evidence-based PTSD treatments.
For clinicians who want a structured foundation in exposure treatment, Prolonged Exposure Therapy training teaches assessment, preparation, imaginal exposure, in-vivo exposure, symptom monitoring, and modifications.
NDIT takes an integrative approach in which clinicians can titrate trauma processing based on the client’s presentation and response.
This can provide additional flexibility when a client needs trauma exposure to proceed more gradually.
3. Working Beyond Verbal Insight
Trauma treatment does not always progress through discussion alone.
Physiological reactions, sensory triggers, emotional activation, dissociation, and conditioned threat responses may continue even after the client has developed substantial insight.
NDIT therefore incorporates multiple avenues for trauma processing rather than relying exclusively on verbal exploration.
For therapists already using EMDR, exposure therapy, somatic strategies, IFS, or cognitive interventions, this can create a broader framework for combining skills without abandoning existing clinical training.
4. Greater Flexibility for Complex Trauma
Complex trauma rarely presents as one isolated symptom.
Clients may experience combinations of avoidance, hyperarousal, dissociation, negative beliefs, relationship difficulties, emotional dysregulation, and physical reactions.
A modular framework allows clinicians to respond to these different needs rather than assuming every client must move through treatment in exactly the same way.
This is especially relevant when therapy has stalled despite the clinician and client having already established insight, rapport, and a clear understanding of the traumatic experiences involved.
Is NDIT a Replacement for EMDR or Other Trauma Therapies?
No.

NDIT is better understood as an integrative trauma-treatment framework that can expand a clinician’s existing toolkit.
EMDR, Prolonged Exposure, CBT, and other established trauma treatments continue to have important roles in clinical practice.
NDIT gives clinicians another way to organize and integrate trauma-treatment strategies when a client needs greater flexibility than a single protocol provides.
The question therefore is not:
Which trauma therapy is best?
A more useful clinical question may be:
What does this particular client need at this stage of treatment?
Expand Your Trauma Treatment Toolkit With NDIT
When trauma therapy stalls, clinicians do not always need to abandon what they are already doing.
They may need additional ways to regulate activation, work with dissociation, titrate exposure, address physiological responses, and integrate techniques from several trauma-treatment approaches.
That is the gap NDIT is intended to help fill.
Mental health professionals interested in developing these skills can explore the Certificate in Neural Desensitization and Integration Training, a 35.25-CE program designed to provide more advanced training in the NDIT framework.
Frequently Asked Questions
What is NDIT therapy?
Neural Desensitization and Integration Training (NDIT) is an integrative, trauma-focused framework designed to help clinicians work flexibly with trauma symptoms. It incorporates concepts and techniques from approaches such as EMDR, exposure-based therapies, IFS, cognitive interventions, somatic strategies, and neuroscience.
How is NDIT different from EMDR?
EMDR is a structured trauma therapy with specific phases and procedures. NDIT is a broader, module-based framework that can incorporate EMDR techniques alongside other trauma-treatment strategies. It is intended to give clinicians more flexibility when a single protocol does not fully meet a client’s needs.
Is NDIT a replacement for EMDR?
No. NDIT is not intended to replace EMDR or other established trauma therapies. Clinicians can use NDIT concepts alongside existing training in EMDR, exposure therapy, cognitive therapy, somatic approaches, and other trauma-focused methods.
Why does trauma therapy sometimes stop working?
Trauma therapy may stall when clients become overwhelmed, dissociate, avoid traumatic material, struggle with nervous system regulation, or continue to experience strong physiological responses despite gaining cognitive insight. In these situations, clinicians may need to adjust the pace or use additional treatment strategies.
Can NDIT be used for complex trauma?
NDIT may be particularly relevant when clinicians are working with complex trauma presentations that involve multiple symptoms, including dissociation, emotional dysregulation, avoidance, physiological activation, and negative beliefs. Its modular structure allows clinicians to adapt their approach based on the client’s presentation.
Can NDIT help clinicians work with dissociation?
NDIT includes strategies related to stabilization, nervous system regulation, body awareness, and titrated trauma processing, which may be useful when dissociation complicates trauma treatment. Clinicians should still assess each client’s needs and work within their professional training and scope of practice.
Does NDIT use exposure therapy?
Exposure-based principles can form part of the NDIT framework, but NDIT is not simply an exposure therapy protocol. Clinicians may adjust the intensity and pacing of trauma processing while integrating exposure with other therapeutic strategies.
Who can take NDIT training?
NDIT training is primarily intended for mental health professionals who work with trauma and PTSD and want to expand their trauma-treatment skills. Eligibility and continuing education requirements can vary by profession and jurisdiction, so clinicians should confirm that a program meets their specific professional needs.
Is NDIT evidence-based?
NDIT is described as an evidence-informed framework that integrates concepts and techniques drawn from established trauma therapies and neuroscience. It should not be presented as having the same independent research base as longer-established treatments such as EMDR or Prolonged Exposure.
What should therapists do when a trauma treatment protocol is not working?
Clinicians may need to reassess the client’s symptoms, readiness, level of activation, dissociation, treatment goals, and response to the current approach. Adjusting pacing, strengthening stabilization skills, or integrating additional evidence-informed techniques may help when progress has stalled.
